
Choosing the right Blood Transfusion Set is a clinical decision, not a purchasing shortcut. The set connects the blood component, administration device, and patient. Each part must support safe, controlled delivery.
A suitable set should match the blood product, transfusion equipment, and facility protocol. Check the tubing, filter, connectors, priming method, and flow requirements before use. The filter should retain harmful clots or debris without unnecessarily slowing the transfusion. Fit matters. A loose connection can cause leakage, contamination, or treatment delays.
Practical experience shows that small details often create larger risks. Nurses may need clear clamps, visible drip chambers, and tubing that remains flexible in busy rooms. Compatibility with infusion pumps also deserves careful review. Some sets perform differently with packed red cells, plasma, or platelets. Not every set works. Product information and manufacturer instructions should guide selection, while qualified professionals confirm local requirements. Independent standards and hospital policies provide stronger assurance than marketing claims.
This guide will compare essential features, common set types, and selection considerations. It will also discuss storage, inspection, and safe handling before transfusion. The recommendations are general, not a replacement for clinical judgment. A careful team may still find gaps after implementation. That is useful. Reviewing near-misses, user feedback, and actual workflow can improve future purchasing decisions. The safest choice is usually the set that fits the product, equipment, patient needs, and verified clinical procedure.
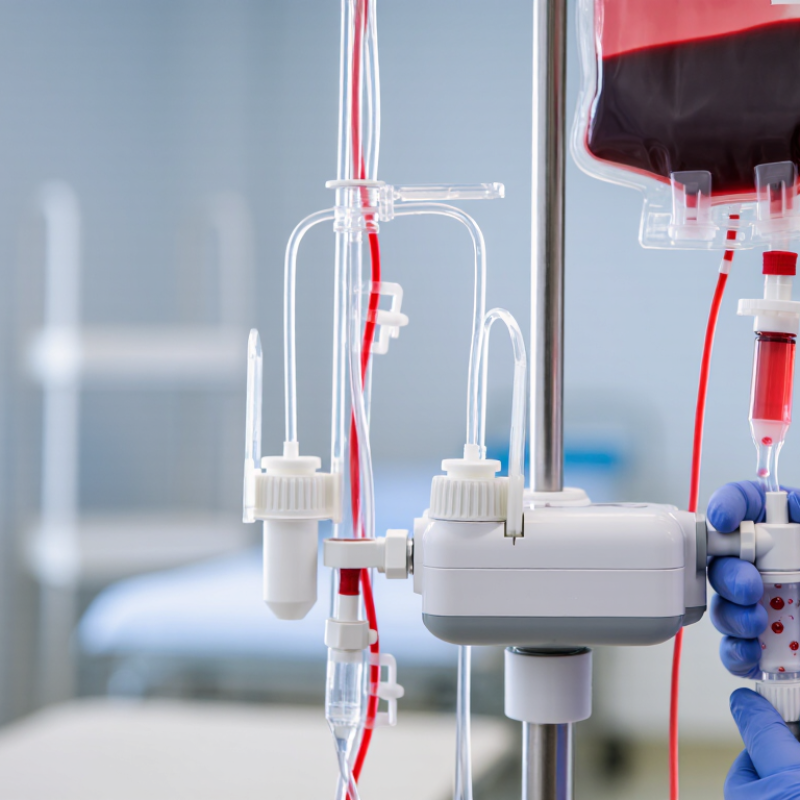
Choosing the right blood transfusion set begins with understanding its main components. A standard set usually includes a piercing spike, drip chamber, tubing, clamp, connector, and an integrated filter. The spike enters the blood container carefully. The drip chamber helps staff observe the flow rate and detect unusual air movement. A filter, commonly rated around 170–260 microns, helps reduce the passage of clots and particulate matter. The tubing must remain clear, flexible, and securely connected.
Tips: Check the package seal, expiry date, filter rating, and connector type before use. Confirm compatibility with the blood container and the facility’s transfusion protocol. Inspect the tubing under good lighting. Do not guess. If any part looks damaged, wet, cloudy, or incomplete, remove it from use and report the concern.
In clinical practice, set selection also depends on the transfusion purpose and expected flow rate. A larger-bore design may support faster administration, while controlled flow can suit patients needing closer monitoring. However, flow depends on more than tubing size. Patient condition, equipment height, venous access, and prescribed limits all matter. Staff should prime the set according to approved procedures and monitor the patient continuously. One detail is often missed: the clamp should be easy to adjust without pulling the line. Selection is not always obvious, so trained professionals should review the complete setup before starting.
How to Choose the Right Blood Transfusion Set?
Matching the set to the procedure begins with the blood component, flow rate, and delivery method. Red blood cell transfusions commonly require a blood administration set with an approved in-line filter. The filter helps reduce clots and cellular debris during administration. Check the required filter range in your facility’s protocol. The filter matters.
For routine gravity transfusion, select tubing designed for blood products and confirm that all connections fit securely. When using an infusion pump, choose a set specifically approved for that pump. A rapid transfusion needs pressure-rated tubing and equipment designed for high flow. Never assume ordinary tubing is suitable. Platelet or plasma procedures may require different handling, especially when reducing product loss or maintaining component quality. Follow the component-specific instructions.
Patient factors also influence the choice. Neonatal and pediatric transfusions may need smaller-volume tubing, calibrated chambers, or syringe-based delivery. A blood warmer requires compatible tubing and careful temperature control. Inspect the package, expiry date, filter, and clamps before use. Confirm the set is intact and sterile. Do not improvise.
A frequent mistake is choosing a familiar set without checking the procedure. That shortcut can affect flow, residual volume, or pump performance. Local policy and current clinical guidance should take priority over habit. If the instructions are unclear, pause and ask a qualified transfusion professional before connecting the set.
Choosing a blood transfusion set is not merely a purchasing decision. The set must match the blood product, equipment, and patient’s clinical needs. Red cells, plasma, platelets, and cryoprecipitate may require different handling. Confirm the prescribed component before opening sterile packaging. Check the required filter, priming volume, tubing length, and connector type. These details affect flow, visibility, and connection security. Do not assume every infusion pump is suitable. Verify pump compatibility, pressure limits, alarms, and blood warmer requirements in the instructions for use. Also confirm compatibility with needleless connectors and monitoring equipment. Small mismatches can delay treatment.
A common mistake is treating compatibility as a box-ticking exercise. It is not. Even experienced staff can overlook an expired set, damaged packaging, or an unsuitable connection. Inspect every package carefully. Follow institutional policy and the manufacturer’s instructions for use. Use only fluids or medications confirmed as compatible with the blood component and transfusion line. Normal saline is commonly accepted, but local protocols control practice. When details seem unclear, pause and ask a qualified transfusion professional.
Tips: Check twice. Match the set to the component. Confirm the filter and pump requirements. Keep the blood label, set details, and checks traceable. Document everything. If equipment feels forced or connections leak, stop and replace it. Never rely on memory alone. Lodged assumptions can be dangerous.
How to Choose the Right Blood Transfusion Set?
Choosing a blood transfusion set starts with the patient’s needs and the transfusion plan. Check that the set is sterile, intact, and approved for blood administration. A reliable set should include secure connections, a clear drip chamber, an adjustable clamp, and a suitable filter. Standard blood filters commonly remove clots, cellular debris, and particulate matter. Filter size still matters, because not every clinical situation has the same requirement. Always follow local protocols and the set’s instructions.
Flow requirements deserve careful attention. A narrow line may slow a rapid transfusion, while excessive pressure can damage the system or create safety concerns. Consider the blood product, venous access, patient condition, and required infusion time. Compatibility with pressure devices must be confirmed before use. Medication ports can look convenient, but medications should not share the line unless the protocol clearly permits it. Small oversights matter.
Tips: Inspect the package before opening. Prime the tubing carefully and remove visible air. Check every connection before starting. Monitor the drip chamber, filter, and patient throughout the transfusion. A perfect checklist does not replace clinical judgment. In practice, flow can change as the filter collects material or the patient moves. Reassess instead of assuming the original rate remains safe.
| Evaluation Dimension | Recommended Specification | Why It Matters | Best Fit by Clinical Situation | Selection Check |
|---|---|---|---|---|
| Blood Component | Use a set specifically intended for blood or blood components, with materials compatible with the component being administered. | Blood components require administration devices that support safe flow, minimize contamination risk, and maintain component integrity. | Red blood cells, plasma, platelets, and cryoprecipitate should be administered according to the facility’s approved protocol. | Confirm that the set is labeled for the intended blood component and is approved for the planned route of administration. |
| Filter Type | A standard blood administration filter with a nominal pore size of approximately 170–260 micrometres. | The filter helps remove clots, fibrin strands, and particulate matter that may be present in the blood component or tubing. | Routine transfusion of red blood cells, plasma, platelets, or other components when no special filtration requirement exists. | Check the filter pore size, effective filter area, and whether the filter is integrated into the blood tubing. |
| Leukocyte Reduction | Do not assume that a standard blood filter provides leukocyte reduction. Use leukocyte-reduced components or a validated leukocyte-reduction filter when clinically indicated. | Standard blood filters remove particulate material but are not designed to reliably remove leukocytes. | Patients with a documented need for leukocyte-reduced components should receive products selected and processed under the applicable clinical protocol. | Verify whether leukocyte reduction is performed before transfusion or requires a separate validated device. |
| Priming and Wetting | The filter and drip chamber should be completely wetted and primed with the compatible blood component or an approved compatible solution. | Incomplete priming may reduce filter performance, introduce air, and interrupt the intended flow. | All transfusions, especially when a small-volume component or a slow infusion rate is planned. | Inspect the chamber and filter before connection; follow the institution’s priming procedure and compatibility rules. |
| Flow Requirement | Select tubing with a suitable internal diameter and a filter capacity that supports the planned rate without excessive resistance. | Flow depends on viscosity, component temperature, needle or catheter size, tubing resistance, patient access, and the use of a pump or pressure device. |
Routine transfusion: standard blood tubing. Rapid transfusion: high-flow, pressure-rated equipment and appropriate vascular access. |
Do not select a set by tubing size alone. Confirm the manufacturer’s validated flow or pressure limits and the facility’s emergency-transfusion protocol. |
| Pressure Compatibility | For pressure-assisted or rapid transfusion, use a set explicitly rated for the intended pressure and flow conditions. | Excessive pressure can damage blood cells, dislodge connections, or cause leakage if the tubing and filter are not designed for that use. | Massive hemorrhage, trauma, surgery, or other situations requiring rapid component delivery. | Check pressure limits, connection security, filter design, and compatibility with the pressure infuser or rapid-transfusion device. |
| Air Management | Use a clear drip chamber, secure connections, and an air-management feature when required by the administration system or protocol. | Air entry can interrupt flow and may create a patient-safety hazard, particularly during pump-assisted or rapid administration. | Any transfusion; enhanced air-management features are especially relevant for pumps, pressure systems, and small-volume infusions. | Prime the line fully, keep connections secure, and verify that the selected set is compatible with the infusion pump if one is used. |
| Connector Design | Use secure, leak-resistant, needle-free or luer-compatible connections as required by the clinical setup and applicable standards. | Reliable connectors reduce leakage, accidental disconnection, contamination, and misconnections. | Routine transfusion, multi-line access, and settings where frequent connection or disconnection is expected. | Confirm connector compatibility with the catheter, extension set, pump, and other components in the administration pathway. |
| Medication Compatibility | Use a dedicated blood line whenever possible. Do not introduce medications into the blood line unless compatibility has been specifically established. | Some medications or solutions may cause hemolysis, clotting, precipitation, or other adverse interactions with blood components. | All blood-component transfusions, particularly when the patient requires concurrent intravenous therapy. | Check the compatibility policy before using the same access line for blood and any medication or non-approved solution. |
| Material and Biocompatibility | Choose blood-contacting materials that are compatible with the component and intended duration of use, with no unnecessary additives or extractables. | Material compatibility supports component quality and reduces the risk of leakage, degradation, or undesirable interaction. | Routine and prolonged transfusion procedures, including use with pumps or warming systems. | Review the product instructions for material compatibility, temperature limits, and use with blood warmers or infusion devices. |
| Visibility and Monitoring | Use transparent tubing and a clearly visible filter and drip chamber. | Visibility allows staff to monitor flow, detect air, observe clot or particulate accumulation, and identify color changes or leakage. | All transfusions, especially those requiring close monitoring or variable flow rates. | Ensure the line is positioned so that the filter, drip chamber, and connections can be inspected throughout administration. |
| Priming Volume and Dead Space | Select a low-dead-space set when conserving blood component volume is important; verify the actual priming volume in the product specifications. | Excessive residual volume may be significant during pediatric, neonatal, or small-volume transfusions. | Neonatal and pediatric transfusion, small-volume aliquots, and situations where minimizing discard is clinically important. | Compare the stated priming volume, filter volume, tubing length, and any additional extension components. |
| Special Temperature Requirements | When warming is indicated, use a blood-warming system and administration set that are validated for that system. | Controlled warming can help prevent hypothermia during rapid or large-volume transfusion; uncontrolled heating may damage blood components. | Rapid transfusion, major hemorrhage, selected neonatal procedures, or clinically indicated temperature management. | Confirm the permitted temperature range, warmer compatibility, alarm function, and monitoring requirements. |
| Single-Use and Change Interval | Use sterile, single-use equipment and replace it according to the facility policy, component type, and applicable instructions for use. | Appropriate replacement limits reduce contamination risk and prevent excessive filter loading or flow restriction. | Every transfusion episode and any situation involving multiple units or components. | Record the start time, follow local replacement intervals, and replace the set if it becomes contaminated, occluded, damaged, or visibly compromised. |
| Final Safety Verification | Use bedside patient identification, component verification, visual inspection, and vital-sign monitoring according to the transfusion policy. | The administration set is only one part of transfusion safety; correct patient, component, route, rate, and monitoring are essential. | Every blood-component administration, regardless of set type or transfusion speed. | Confirm patient identity, component details, expiry, appearance, compatibility requirements, prescribed rate, and observation plan before starting. |
A blood transfusion set is a safety device, not merely tubing. Start by checking its intended use, approved standards, and compatibility with the blood component. ISO 1135-4 addresses sterile, single-use equipment for transfusion. Local regulations may add requirements. Confirm them before purchase or clinical use.
The World Health Organization reported 118.5 million blood donations globally in 2021. That scale makes consistent equipment control essential.
Inspect the package under good lighting. The seal should be complete, dry, and free from punctures. Check the lot number, expiry date, storage conditions, and sterilization information.
Do not use a set with cloudy tubing, loose caps, wet packaging, or damaged ports. It should include the correct filter, commonly within the 170–260 micrometre range, according to local instructions. Small defects matter.
Before connection, verify patient identity, blood label, prescription, and compatibility checks. Prime the line only with an approved solution. Avoid unsuitable fluids that can damage cells or trigger clotting.
Keep the system closed whenever possible. Follow the facility’s time limits and monitoring procedure. A checklist helps, but it cannot replace trained judgment.
I have seen teams trust intact packaging too quickly; sterility does not confirm correct selection. WHO guidance and national transfusion standards should guide every final decision.
Match the set to the blood component, flow rate, and delivery method. Red blood cells usually need approved tubing with an in-line filter. The filter matters. Follow local instructions before connecting anything.
Common blood filters remove clots, cellular debris, and particles. Many filters range from 170 to 260 micrometres. Confirm the required range locally. Do not guess from appearance.
No. Rapid transfusion requires pressure-rated tubing and compatible equipment. Ordinary tubing may restrict flow or create safety concerns. Never assume compatibility.
Inspect the seal under good lighting. Look for punctures, moisture, cloudy tubing, loose caps, or damaged ports. Check the expiry date, lot number, and storage conditions. Small defects matter.
Use tubing specifically approved for that pump. Confirm the pump and set are compatible before starting. A familiar set may seem convenient. That shortcut can affect flow and performance.
They may require smaller-volume tubing, calibrated chambers, or syringe-based delivery. Patient size and prescribed volume influence the choice. Tiny volumes need careful control.
Use tubing compatible with the warmer and control temperature carefully. Check the equipment instructions before connection. Do not improvise. Temperature errors can harm the transfusion process.
Check the drip chamber, filter, connections, and patient regularly. Flow may change as material collects in the filter. Movement can also alter the rate. Reassess instead of assuming.
Only when the clinical protocol clearly permits it. Medication ports may look convenient, but compatibility is not automatic. Use an approved solution for priming. Unsuitable fluids can damage cells or cause clotting.
Pause before connecting the set. Ask a qualified transfusion professional. A checklist helps, but it cannot replace judgment. I might trust intact packaging too quickly; correct selection still needs confirmation.
Choosing the right Blood Transfusion Set is essential for ensuring a safe, efficient, and controlled transfusion. The selection should begin with an understanding of the set’s main components, including tubing, connectors, drip chambers, clamps, and filters. The set must match the intended procedure, whether it is used for whole blood, red cells, plasma, or other compatible blood products. It should also connect securely with the collection container, transfusion device, and vascular access equipment.
Before use, evaluate the filter type, flow capacity, safety features, and priming requirements to support smooth delivery and reduce the risk of clots, air entry, leakage, or contamination. Always verify that the product is compatible with the blood component and the clinical equipment being used. Finally, check packaging integrity, expiration information, labeling, storage conditions, and applicable quality standards. Proper preparation and careful inspection help healthcare professionals select an appropriate set and promote safe transfusion practices.
